Choosing an intraoral scanner is not just a matter of comparing prices or chasing the newest model. The right digital impression systems must fit your clinical workflow, restoration mix, and team’s experience. A scanner that feels fast during a demonstration may behave differently when capturing a wet molar margin or a full-arch case.
Prosthodontist and digital dentistry researcher Dr. Markus B. Blatz has emphasized a patient-centered approach to digital care. In paraphrase, his guiding point is that technology should support predictable treatment, not become the goal itself. That distinction matters. A clear scan can reduce repeat impressions, but results still depend on preparation quality, isolation, scanning technique, and laboratory communication. Small details count.
This guide presents seven practical tips for evaluating systems: assess image accuracy, handling, software, integration, training, support, and total cost. Look closely at how the scanner captures tight interproximal spaces, displays missing data, and exports files to your lab. Ask for a hands-on trial using cases similar to your own. Check whether staff can learn the workflow without slowing appointments. Fit matters.
No single system is ideal for every practice. Some comparisons are difficult, and advertised speed does not always translate into smoother visits. The recommendations ahead are meant to sharpen your questions, not replace clinical judgment. A careful choice can make digital impressions more consistent for clinicians, technicians, and patients.
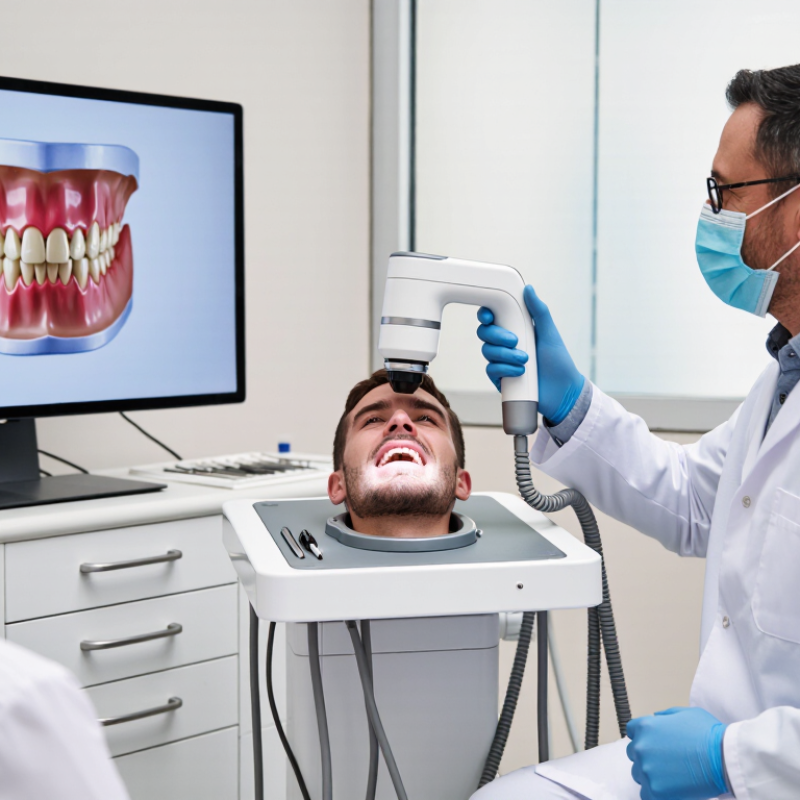
Choosing an intraoral scanner starts with the work your clinic actually performs. List common cases: single crowns, short bridges, implant restorations, orthodontic records, and full-arch appliances. Then note where scans go next, such as laboratory design, chairside milling, or aligner planning. A 2018 review in the Journal of Prosthodontic Research found digital impressions often reduced impression-taking time, but accuracy varied by case type and scan length. That matters: a scanner that works well for a crown may need a different scanning strategy for a full arch.
Tip: Map one routine case from preparation to delivery. Include who scans, who checks margins, how files reach the lab, and what happens when a scan needs correction. Small workflow gaps can erase time savings.
Define the digital impression types you require before comparing systems. Confirm support for prepared teeth, implants, edentulous areas, bite records, and full-arch capture, as relevant to your caseload. Evidence reviews generally report more predictable results for shorter-span restorations than for full-arch scans, where stitching errors can accumulate.
Ask for a demonstration using your actual clinical steps, not only a polished sample case. I still find it easy to underestimate staff training. That part deserves a real budget.
Keep a short trial log: rescans, chairside minutes, file corrections, and lab feedback. Those details are more useful than a feature list.

A digital impression system should be judged by measured accuracy, not a polished demonstration. ISO 20896-1:2019 provides methods for assessing digital impression devices. It separates trueness, closeness to a reference, from precision, repeatability across scans. The standard offers a testing framework, not a universal clinical pass mark.
Renne and colleagues’ 2017 in vitro comparison of seven scanners reported trueness values of about 39–69 micrometers and precision values around 37–44 micrometers. These figures show why both measures matter: a scanner may repeat the same error consistently. Ask whether tests used a short model or a full arch, and whether scan paths and reference equipment were controlled. Small details count. A wet surface, reflective material, or operator movement can affect results in practice.
When comparing systems, request the test protocol, sample size, and variability—not just the best average. Check whether the report follows ISO 20896-1:2019 and uses clinically relevant scan lengths. A single bench result cannot predict every patient’s mouth. I would also repeat scans with different operators; this takes time, and results may be less tidy than the brochure suggests. That discomfort is useful. It reveals whether the workflow is genuinely repeatable.
A full-arch scan can look seamless on screen and still contain accumulated error. Ask for trueness and precision results in micrometers, measured across the whole arch—not a single tooth. In a 2013 in-vitro study, Ender and Mehl reported mean trueness values of 32.4 ± 9.8 μm for digital impressions and 20.4 ± 2.2 μm for conventional impressions. These figures describe specific methods under laboratory conditions, not every current scanner. Still, they show why a headline accuracy claim needs its test method attached.
Request the study design: Was the scan of a model or a patient? How long was the arch, and where were deviations measured? A 30 μm error near an incisor may not predict distortion at the opposite molar. Ask for color deviation maps and repeat-scan results, too. Look for performance across several operators, since hand speed and scan path can change outcomes. Small details matter. A glossy demonstration is not a protocol.
One awkward truth: published numbers are difficult to compare when studies use different reference scanners, software, and landmarks. Ender and Mehl’s paper in the Journal of Prosthetic Dentistry is useful context, not a universal pass mark. Before choosing a system, request raw full-arch data and the complete measurement conditions. If a supplier gives only a headline number, ask what was measured—and where.
Measure scan speed under consistent conditions: the same arch, scan path, and operator. A 2014 peer-reviewed clinical comparison by Yuzbasioglu et al. reported mean impression-taking times of 248.48 seconds for digital scanning and 605.93 seconds for conventional impressions. That finding is useful, but it is not a promise for every clinic. Case complexity, moisture, operator experience, and rescanning can change the result. Speed alone misleads.
Check the field of view alongside speed. A broader capture area may record more surface per pass, but only if overlapping images stitch reliably. Ask how the system handles posterior areas, deep margins, and sudden movement. Then time the full appointment, not just the scan: setup, retraction, bite registration, image review, and corrections all occupy chair time. Record these steps across several real cases. Small differences add up. One awkward scan can erase a quick start, and that is worth admitting. Compare median times, too; a single unusually easy case can make a system look faster than it feels in daily practice.
Use the same scan protocol and case type when comparing systems. The figures below are measurement methods and practical evaluation guidance—not guaranteed device performance; results vary with operator technique, anatomy, software, and workflow.
| Tip | What to Measure | Useful Comparison Data | How to Validate It |
|---|---|---|---|
| 1. Compare scan speed | Active scanning time for a defined scan, such as one prepared arch or a full-arch scan. | Record elapsed time in minutes and seconds. Separate active scanning from setup, image processing, and rescanning; there is no single scan-time figure that applies to every case. | Use the same arch, scan path, operator experience, and completion criteria for each system. Time several repeat scans rather than relying on a single demonstration. |
| 2. Check field of view | The capture window and depth the scanner can image in one acquisition, as specified in its technical documentation. | Compare the stated field-of-view dimensions and depth in millimetres, where published. A wider capture window may reduce repositioning, but does not by itself establish accuracy or ease of use. | Test access around posterior teeth, interproximal areas, and the gingival margin. Confirm that the system can capture the intended anatomy without repeated repositioning. |
| 3. Measure patient chair time | Total time from seating the patient to finishing the digital impression workflow. | Log setup, scanning, rescanning, bite registration, and any required retakes separately. Compare the median time for the same procedure across multiple appointments. | Use cases of similar complexity and include normal clinical steps. Keep active scan time distinct from total chair time so workflow differences are visible. |
| 4. Evaluate accuracy | Trueness (closeness to a reference) and precision (repeatability across scans). | Review independent studies that report measurement error in micrometres or millimetres and identify the scan type tested. Results from a short-span scan should not be assumed to represent a full arch. | Check whether the study describes its reference method, scan protocol, sample size, and clinical application. Ask for evidence relevant to the restorations or appliances your practice makes. |
| 5. Track rescans and missing data | First-pass acceptance rate, incomplete areas, and number of rescans needed per case. | Calculate first-pass acceptance as accepted scans divided by total attempted scans. Record the reason for each rescan, such as stitching gaps, saliva, motion, or inaccessible anatomy. | Review a consistent set of cases and operators. A shorter initial scan may not save time if it leads to more correction or repeat scanning. |
| 6. Assess tip size and handling | Tip dimensions, visibility, cable or wireless handling, and comfort of access in the mouth. | Compare the manufacturer-stated tip dimensions and available tip options. Also check the documented cleaning, disinfection, or sterilization method and reusable-tip cycle limits. | Have clinicians test posterior access and patient comfort. Follow the system’s instructions for use; do not assume that tips are interchangeable or compatible with every reprocessing method. |
| 7. Confirm workflow and data access | File export options, software compatibility, processing time, and the steps needed to submit a case. | List supported file formats, export restrictions, integration requirements, and any recurring software or service costs. Confirm whether the intended laboratory or design workflow accepts the files. | Run a complete test case from scan to submission. Verify that the receiving workflow can open the file and that staff can retrieve, review, and transfer scans when needed. |
Compare CAD/CAM compatibility before comparing scanner prices. Confirm whether files export in open formats, connect directly to your design software, and preserve margins without manual cleanup. Ask for a live test using a prepared tooth and a full-arch scan. Small workflow gaps become daily costs. A review by Mangano et al. in BMC Oral Health found that scanner accuracy depends on equipment, operator technique, and clinical conditions. That matters when evaluating vendor claims: published results may not reflect your team’s learning curve or typical patient cases.
Tip: Request a written compatibility list and test the exact file path, including lab transfer. Check whether updates, cloud storage, and support require recurring fees. A scanner with a lower purchase price may cost more over five years. Add hardware, software subscriptions, training time, service contracts, replacement parts, and any export charges. The ADA’s 2023 Survey of Dental Practice tracks practice expenses across categories; use your own expense records to estimate what a new workflow will displace or add.
Tip: Build a simple five-year ownership sheet. Enter annual fees and expected scan volume, then calculate cost per case. Include realistic downtime. Your estimate will still be imperfect; usage and repair needs can change. Ask for a trial period, and document who owns stored scans if you switch systems.